

As a psychotherapist working with people in Australia, I’ve found that understanding how past experiences shape our present is key to healing. The structural dissociation model offers a way to look at this, especially when trauma is involved. It helps explain why sometimes, our minds feel split, and different parts of us seem to take over. I want to share some insights into this model, how it shows up in practice, and how we can work with it to support clients on their journey towards feeling more whole.
Key Takeaways
- The structural dissociation model helps us understand how trauma can lead to a sense of being fragmented, with different ‘parts’ of ourselves emerging.
- Dissociation isn’t always a problem; it exists on a spectrum from everyday experiences like daydreaming to more complex responses to trauma.
- Early, overwhelming trauma can cause the mind to ‘split off’ experiences, creating separate parts or alters to cope.
- This model highlights the role of a ‘core self’ and various dissociated parts, often separated by an ‘amnesiac barrier’.
- Therapeutic approaches informed by this model focus on working with these parts and helping to integrate dissociated experiences for a more cohesive sense of self.
Understanding the Structural Dissociation Model
What is the Structural Dissociation Model?
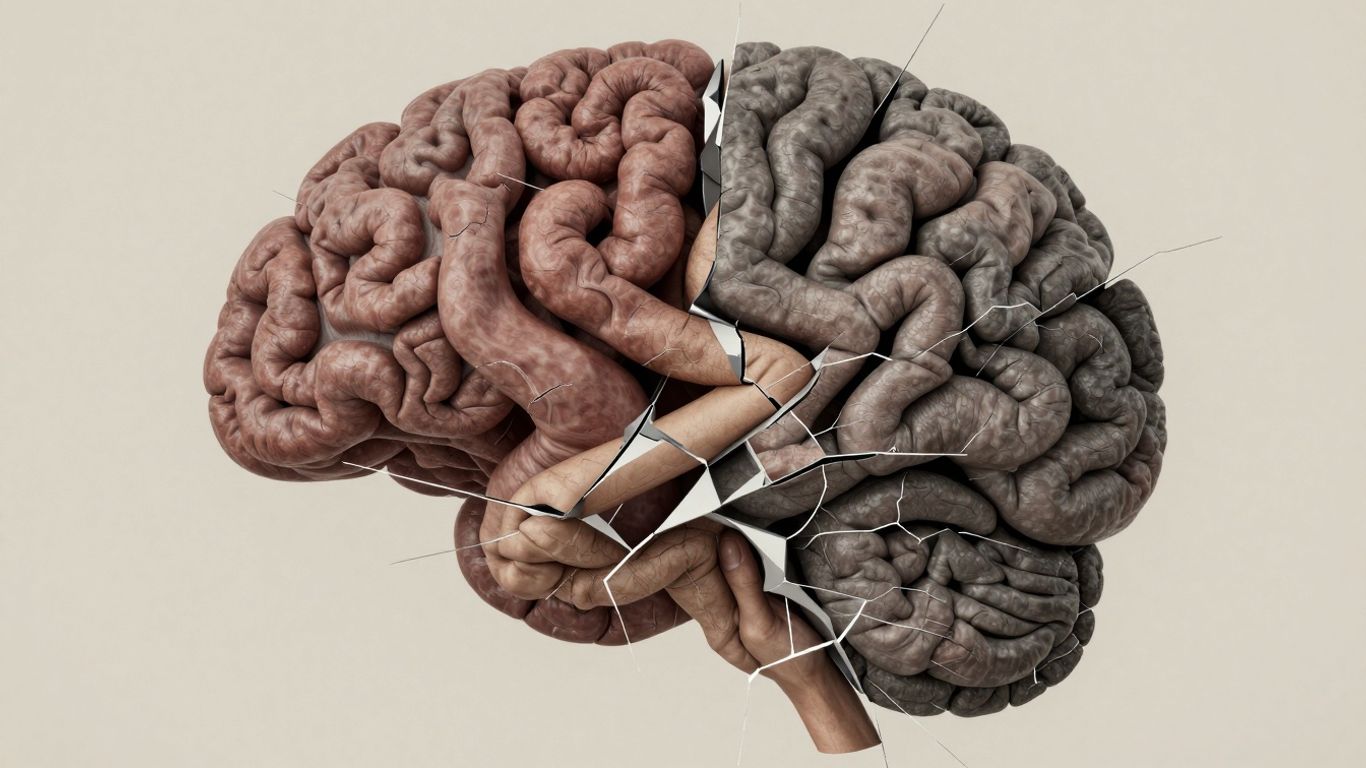
So, what exactly is this Structural Dissociation Model I’ve been hearing about? Essentially, it’s a way of understanding how our minds can split or fragment, particularly in response to overwhelming experiences, like trauma. It’s not about having multiple personalities in the way you might see in movies, but rather about how different parts of ourselves can become disconnected. Think of it like a very complex coping mechanism that the mind develops when things get too much to handle all at once. This model helps us see dissociation not as a strange anomaly, but as a spectrum of experiences.
A Continuum of Dissociation
It’s really important to get that dissociation isn’t an all-or-nothing thing. It exists on a continuum, meaning it can range from very mild, everyday experiences to much more complex presentations. We all do it to some extent. For example, have you ever been driving and suddenly realised you don’t remember the last few kilometres? Or perhaps you’ve been so engrossed in a book or a conversation that you completely lost track of time? That’s a form of dissociation, a mild disconnection from your immediate surroundings. The Structural Dissociation Model helps us map out this spectrum, showing how these everyday experiences can, under certain circumstances, become more pronounced and impactful.
The Role of Trauma in Dissociation
When we talk about the Structural Dissociation Model, trauma is almost always at the centre of the conversation. Severe or prolonged trauma, especially during childhood, can overwhelm a person’s capacity to cope. In these situations, the mind might ‘split off’ certain memories, feelings, or aspects of identity to protect the core self from unbearable pain. This ‘splitting off’ is a survival strategy. The more intense and prolonged the trauma, the more likely it is that the mind will develop more significant dissociative responses. Understanding this connection is key to grasping why dissociation occurs and how it can affect a person’s life. It’s a way the mind tries to manage the unmanageable, and it can lead to the development of distinct parts or ‘alters’ within a person’s experience, which is a core concept in understanding Dissociative Identity Disorder.
Normal Versus Pathological Dissociation
It’s easy to think of dissociation as something that only happens to people with very complex conditions, but the truth is, we all experience it to some degree. It’s a bit like a spectrum, and understanding where everyday experiences fit compared to more challenging ones is key.
Everyday Dissociative Experiences
Think about those moments when you’re driving along a familiar road and suddenly realise you don’t remember the last few kilometres. Or perhaps you’ve been so engrossed in a book or a movie that you’ve completely lost track of time and your surroundings. These are common, everyday examples of dissociation. They happen when our minds are focused intensely on an internal process, like daydreaming, or when we’re doing something so familiar that our brain can handle it on autopilot. These brief moments are usually harmless and don’t really get in the way of our daily lives. They’re a normal part of how our minds work, helping us to tune out distractions when needed.
When Dissociation Becomes Problematic
So, when does this natural ability become something more concerning? It shifts from ‘normal’ to ‘pathological’ when it starts to significantly disrupt a person’s life. This can happen when dissociative experiences become more frequent, more intense, or when they’re directly linked to overwhelming events, particularly trauma. Instead of just a brief lapse in awareness, it might involve significant gaps in memory, feeling detached from oneself or reality, or experiencing a sense of being a different person. This is where dissociation starts to impact relationships, work, and a person’s overall sense of self and safety. It’s a sign that the mind is using this coping mechanism to protect itself from unbearable experiences, but the cost is a fragmentation of consciousness that makes everyday functioning difficult. Understanding dissociation is a crucial first step in supporting clients through their healing journey.
The Spectrum of Dissociative Symptoms
It’s helpful to see dissociation not as an all-or-nothing thing, but as a range. On one end, we have those fleeting daydreams or that ‘highway hypnosis’ we talked about. As we move along the spectrum, we might see more pronounced memory issues, like forgetting chunks of time, or feeling like you’re watching yourself from outside your body. Further along, people might experience distinct ‘parts’ or ‘alters’ that seem to have their own identities and memories. The most complex presentations, like Dissociative Identity Disorder, represent the far end of this spectrum. It’s important to remember that even severe dissociative symptoms are often a response to overwhelming experiences, a testament to the mind’s incredible, albeit sometimes overwhelming, capacity to cope. The key difference lies in the degree of disruption and distress these experiences cause.
The Origins of Structural Dissociation
Early Childhood Trauma and Its Impact
When we talk about the origins of structural dissociation, we’re really looking at how overwhelming experiences in early childhood can shape a person’s sense of self. It’s not about blaming anyone, but understanding the incredible ways the mind tries to cope when things get too much. Imagine a little kid facing something truly terrifying, something they can’t escape or understand. Their brain, in a bid to protect them, might do something pretty remarkable: it splits off the part that’s experiencing the horror from the part that’s trying to carry on.
This splitting off is a survival mechanism, pure and simple. It’s like creating a temporary emergency exit for the mind. The younger the child and the more intense and repeated the trauma, the more likely this splitting is to happen. It’s not a conscious choice; it’s an automatic response to unbearable pain. This is how the foundations for different ‘parts’ or ‘alters’ can begin to form, each holding onto different pieces of the experience.
The ‘Splitting Off’ Mechanism
So, how does this ‘splitting off’ actually work? Think of it like this: when a child experiences something so traumatic that their conscious mind can’t process it, the mind essentially divides. One part of the consciousness has to endure the event, while another part, often referred to as the ‘core self’, is shielded from awareness. This creates a kind of amnesiac barrier between these parts, keeping them separate. It’s a way for the child to survive the moment, but it sets up a pattern. If more trauma occurs, the mind can resort to this same strategy, sending out a previously created part to deal with the situation while the core remains protected. This is a key concept in understanding how dissociation develops.
The Development of ‘Parts’ or ‘Alters’
Over time, with repeated trauma, these split-off parts can become more defined. They aren’t just fleeting thoughts; they can develop their own ways of experiencing the world, their own memories, and even their own ways of behaving. We often refer to these as ‘parts’ or ‘alters’. It’s important to remember that these parts aren’t separate people in the way we usually think of them. They are fragments of a single person’s consciousness, each created to manage specific aspects of life or trauma that the core self couldn’t handle alone. The degree to which this happens can depend on a few things:
- The severity and nature of the traumatic experiences.
- The child’s own creativity and capacity for imaginative coping.
Essentially, the mind builds these protective roles to manage tasks and pain, allowing the person to continue functioning on some level, even in the face of immense difficulty.
Key Components of the Structural Dissociation Model
Right, so we’ve talked a bit about what structural dissociation is and how trauma can lead to it. Now, let’s get into the nitty-gritty of the model itself. It’s built on a few core ideas that help us understand how people who’ve experienced significant trauma might experience the world and themselves differently.
The Core Self and Its Role
Think of the ‘core self’ as the original, whole person you were before trauma significantly impacted your life. It’s the part of you that holds your fundamental sense of being, your core identity. In the context of structural dissociation, this core self can become disconnected or ‘walled off’ from experiences that are too overwhelming to process. It’s not that this part disappears, but rather that it’s protected from the full impact of traumatic events. This protection is a survival mechanism, a way for the mind to keep functioning when faced with unbearable situations.
Understanding Different ‘Parts’
When trauma happens, especially repeatedly and at a young age, the mind might split off different aspects of experience – like memories, emotions, or even skills – into separate ‘parts’ or ‘alters’. These aren’t separate people in the way we usually think of them, but rather different ways of being that hold specific experiences or functions. For example, one part might hold the memory of a traumatic event, another might manage daily tasks, and yet another might hold intense emotions like fear or anger. These parts develop to help the person cope with overwhelming situations by compartmentalising the distress.
It’s helpful to see these parts not as something ‘wrong’, but as adaptive responses to extreme circumstances. They were created to help the person survive.
- Parts holding trauma memories: These parts often carry the emotional and sensory details of distressing events.
- Parts managing daily life: These might appear more functional and handle everyday responsibilities.
- Parts holding intense emotions: These can be the ‘feeling states’ that are too much for the core self to bear.
- Protective parts: These might act out in ways that seem aggressive or defiant, but their intention is to keep the person safe.
The Amnesiac Barrier
This is a really important concept. The ‘amnesiac barrier’ is essentially the gap in memory or awareness between these different parts. It’s what prevents the parts from having full access to each other’s experiences, memories, and emotions. So, the part of you that’s going about your day might have no conscious memory of what another part experienced during a traumatic event, or even what happened yesterday. This barrier is crucial for maintaining a sense of continuity for the parts that are functioning, but it also creates significant challenges in daily life, leading to confusion, memory gaps, and a feeling of not being fully present or in control.
This separation, maintained by amnesiac barriers, is a key feature of structural dissociation. It’s how the mind tries to keep overwhelming experiences from flooding the entire system, allowing for survival, but at the cost of internal coherence and a unified sense of self.
Recognising Dissociative Symptoms in Practice
Sometimes, when I’m working with clients, it becomes clear that dissociation is playing a big role in how they experience the world. It’s not always obvious at first, and it can show up in a few different ways. Understanding these signs is key to helping people move forward.
Common Symptom Clusters
When we talk about dissociation, it’s helpful to think about clusters of symptoms. These aren’t hard and fast rules, but more like patterns that often appear together. It’s like finding a few puzzle pieces that fit nicely to give us a clearer picture.
- Post-Traumatic Stress Symptoms: This can include things like trouble sleeping, or feeling like you’re reliving a difficult experience. Concentration can also be a challenge, and sometimes people experience physical symptoms that don’t have a clear medical cause.
- Dissociative Symptoms: These might involve gaps in memory, especially around childhood, or feeling like you’re in a trance. Sometimes people notice sudden shifts in how they’re acting or feeling, or they might hear voices in their head. There can also be a feeling of being controlled by someone else.
- Affective Symptoms: This is where we see big mood swings. People might experience intense anger, deep sadness, or overwhelming anxiety. Sometimes, emotions can feel muted, or there’s a sense of being completely numb, like going through the motions without really feeling anything.
Post-Traumatic Stress Symptoms
When someone has experienced trauma, their body and mind can stay on high alert. This can lead to a range of symptoms that might look like post-traumatic stress. I often ask about:
- Sleep Disturbances: Difficulty falling asleep, staying asleep, or having nightmares.
- Flashbacks: Feeling like a traumatic event is happening again, complete with sights, sounds, and feelings.
- Concentration Difficulties: Trouble focusing on tasks, conversations, or even simple instructions.
- Physical Symptoms: Unexplained aches, pains, fatigue, or digestive issues that don’t seem to have a physical origin.
Dissociative and Affective Symptoms
Beyond the stress response, dissociation itself can manifest in distinct ways. It’s about how consciousness, memory, and identity are affected. These symptoms are often the mind’s way of coping with overwhelming experiences.
Here are some common signs I look for:
- Memory Gaps: Significant periods of time that a person can’t recall, especially concerning personal history or traumatic events.
- Trance-like States: Appearing spaced out, disconnected from their surroundings, or lost in thought.
- Sudden Shifts (Switches): Noticeable changes in behaviour, mannerisms, speech, or even physical appearance that seem to come out of nowhere.
- Internal Voices: Hearing voices or sounds within one’s mind that aren’t external.
- Feeling Detached: A sense of observing oneself from outside the body, or feeling like the world isn’t real.
Affective symptoms often go hand-in-hand with these. This can include:
- Intense Mood Swings: Rapid shifts between emotions like depression, anger, or anxiety.
- Emotional Numbness: A lack of feeling or appearing robotic, as if disconnected from one’s own emotions.
It’s important to remember that these symptoms exist on a spectrum. What might be a fleeting experience for one person could be a persistent challenge for another. Understanding these patterns helps us approach therapy with more clarity and compassion, supporting people on their unique healing journey. If you’re curious about how these symptoms are classified, the DSM-5-TR offers detailed diagnostic criteria.
The Structural Dissociation Model and DID
Dissociative Identity Disorder Explained
When we talk about the structural dissociation model, it’s impossible not to touch on Dissociative Identity Disorder (DID), formerly known as Multiple Personality Disorder. It’s the most extreme end of the dissociation spectrum, and understanding it really highlights how the mind can split under immense pressure. Think of it like a dam holding back a huge amount of water – if the pressure gets too much, the dam can break, and the water rushes out in different directions. In DID, the ‘water’ is the person’s sense of self, and the ‘breaks’ are the different identities or ‘parts’ that emerge.
DID is essentially a way the mind copes with overwhelming trauma, particularly when it happens repeatedly during early childhood. It’s not a choice, and it’s not something people do to be difficult. It’s a survival mechanism that develops when a child experiences things so horrific they can’t be processed by a single, integrated consciousness. The mind, in a desperate bid to protect the core self, splits off these unbearable experiences and the feelings associated with them into different parts.
How DID Develops Through Dissociation
The development of DID is deeply tied to the dissociative process. When a child faces trauma that’s too much to handle, their mind can ‘split off’ from the experience. This isn’t like forgetting where you put your keys; it’s a more profound separation of consciousness, memory, and identity. This ‘splitting off’ creates distinct parts, each holding different aspects of the person’s experience, memories, and emotions. Over time, especially if the trauma continues, these parts can become quite separate, almost like distinct individuals living within one body.
This process often involves an ‘amnesiac barrier’ forming between these parts. This barrier prevents the different parts from knowing about each other or the traumatic experiences they hold. It’s a way for the mind to compartmentalise the pain, allowing the person to function on a day-to-day basis, even if it’s a highly fragmented way of functioning.
Distinguishing Between DID and Other Dissociative Experiences
It’s important to remember that dissociation exists on a continuum. Many people experience mild dissociative moments, like daydreaming or getting lost in a book – we call this normal dissociation. It’s fleeting and doesn’t disrupt life much. Then there are more significant dissociative experiences that can arise from trauma, which might include memory gaps or feeling detached. DID is at the far end of this spectrum. It’s characterised by the presence of two or more distinct identities or personality states that recurrently take control of the person’s behaviour, along with significant memory gaps that go beyond ordinary forgetfulness.
Here’s a quick way to think about the differences:
- Everyday Dissociation: Daydreaming, ‘highway hypnosis’ – brief, not disruptive.
- Trauma-Related Dissociation: Feeling detached, memory gaps related to specific events, flashbacks.
- Dissociative Identity Disorder (DID): Presence of multiple distinct identities, significant amnesia between parts, often stemming from severe, early childhood trauma.
It’s the degree of fragmentation, the presence of distinct identities, and the extent of amnesia that really sets DID apart from other dissociative experiences. It’s a complex condition that requires careful assessment and understanding.
Therapeutic Approaches Informed by the Model
When working with people who have experienced trauma, especially complex trauma, the structural dissociation model offers a really helpful framework. It guides how I approach therapy, focusing on the different parts of a person that may have developed to cope with overwhelming experiences. My aim is always to work collaboratively, respecting each part and helping the person build a more integrated sense of self.
Working with ‘Parts’ in Therapy
Think of these ‘parts’ not as separate people, but as different ways a person has learned to be and respond to the world, especially when things felt unsafe. In therapy, we don’t try to get rid of these parts. Instead, we aim to understand them, acknowledge their role in survival, and help them communicate with each other and with the ‘core self’. It’s about building bridges between these different experiences and feelings.
Here’s a general idea of how we might work together:
- Identify and Acknowledge: Gently exploring and naming the different parts that show up, without judgment. This might involve noticing different feelings, thoughts, or even physical sensations that seem to come from different places within.
- Understand Their Role: Each part likely developed for a reason, often to protect the person from unbearable pain or to carry out tasks that the main awareness couldn’t handle. We explore what each part’s job was and still is.
- Facilitate Communication: Helping these parts talk to each other and to the ‘core self’. This can reduce internal conflict and create a sense of inner harmony.
- Build Safety: Ensuring that the person feels safe enough to explore these different aspects of themselves. This is paramount, as revisiting difficult experiences needs to be done carefully.
Integrating Dissociated Experiences
Integration isn’t about erasing memories or experiences. It’s about helping the different parts of a person’s experience come together in a way that feels more whole and less fragmented. When dissociation happens, it’s like parts of a person’s life story get separated. Our work together is about gently weaving these threads back into a coherent narrative.
This process often involves:
- Processing Traumatic Memories: Carefully working through memories that were too overwhelming to process at the time they occurred. This is done at a pace that feels manageable for the person.
- Connecting Emotions: Helping to link emotions with the experiences they belong to, so that feelings are understood rather than overwhelming or absent.
- Developing a Coherent Narrative: Creating a life story that includes all experiences, even the difficult ones, in a way that makes sense to the person now.
The goal is not to forget what happened, but to change the impact of what happened, so that it no longer dictates how a person lives their life today. It’s about reclaiming agency and a sense of self that isn’t solely defined by past trauma.
Building a Coherent Sense of Self
Ultimately, the therapeutic journey aims to help people develop a stronger, more unified sense of self. This means feeling more connected to their own thoughts, feelings, and body, and experiencing a greater sense of continuity in their life. It’s about moving from a place of fragmentation to one of wholeness, where all the different parts of the self can coexist and contribute to a richer life.
This might involve exploring creative ways to express oneself, such as through art therapy, to help connect with emotions and experiences that are hard to put into words. The focus is always on the person’s unique journey and building a sense of self that feels authentic and resilient.
Challenges and Nuances in Applying the Model
Complexities of Highly Fragmented Systems
Working with the structural dissociation model is generally pretty straightforward when clients present with a few distinct ‘parts’. But, let’s be real, sometimes the picture is far more complex. I’ve encountered clients whose experiences feel like a thousand tiny pieces, each with its own way of seeing the world and reacting to things. It’s like trying to put together a jigsaw puzzle where half the pieces are missing and the other half are from a completely different puzzle. The sheer number of dissociated parts can be overwhelming, both for the client and for me as the clinician. It makes mapping out the system and understanding the relationships between these parts a real challenge. Sometimes, it feels like I’m just scratching the surface, and I have to remind myself that progress isn’t always linear. It’s about finding a way to connect with any part that’s willing to engage, even if it’s just for a moment.
The Role of Creativity in Dissociation
It’s fascinating, and sometimes a bit confronting, to consider how creativity plays a role in dissociation. The more imaginative a person is, the more elaborate their dissociative structures can become. Think of it like a really talented artist who can create incredibly detailed worlds in their mind. When trauma hits hard, that same creative capacity can be used to build walls and separate experiences so effectively that the core self is shielded from unbearable pain. This is a survival mechanism, pure and simple. However, it means that when we’re working therapeutically, we’re often dealing with incredibly intricate internal landscapes. It’s not just about understanding the ‘parts’, but appreciating the ingenuity of the system that was built to protect the person. This can make understanding the underlying structure of their experience a complex but vital part of the healing process.
Navigating Therapeutic Resistance
Resistance in therapy isn’t always about a client being difficult; often, it’s a sign that a part of them is doing its job to keep them safe. When we’re working with dissociation, this can manifest in unique ways. A part might emerge that is deeply suspicious of therapy, or perhaps one that actively tries to sabotage progress because it believes safety lies in staying exactly as things are. It’s a delicate dance. My approach is to acknowledge and validate the protective function of that resistance, rather than fighting against it. Sometimes, it means slowing down, spending more time building trust, or even working with the resistant part directly to understand its fears. It’s about recognising that these internal dynamics are often deeply ingrained, and change requires patience and a gentle, persistent effort.
Here are some common ways resistance might show up:
- Amnesia: Forgetting sessions or key therapeutic discussions.
- Internal Conflict: Different parts expressing opposing desires about therapy.
- Avoidance: Changing the subject, arriving late, or cancelling appointments.
- Skepticism: Expressing doubt about the possibility of change or the therapist’s competence.
Sometimes, the most challenging aspects of applying this model aren’t about the theory itself, but about the lived reality of people’s experiences. The internal world can be incredibly complex, and our attempts to understand and help can sometimes feel like trying to map an ever-shifting territory. It requires a lot of humility and a willingness to learn from the client’s internal wisdom.
The Structural Dissociation Model in Australian Clinical Settings
Adapting the Model for Local Practice
When I first started working with the structural dissociation model, I found it really helpful to think about how it fits within our Australian context. It’s not a one-size-fits-all approach, and what works for one person might not work for another. We need to be mindful of cultural nuances and the diverse experiences of people seeking support here. For instance, understanding how trauma might be experienced differently across various cultural groups is key. It’s about taking the core principles of the model and making them accessible and relevant to the people we work with every day.
Supporting Clients Through Their Healing Journey
My experience has shown me that supporting clients through their healing journey using this model is a process that requires patience and a deep sense of collaboration. It’s about helping people understand that their experiences, even the most fragmented ones, are survival responses. We can work together to:
- Acknowledge and validate the existence and purpose of different ‘parts’ or dissociative states.
- Gently explore the memories and emotions held by these parts, without overwhelming the client.
- Build bridges of communication between these parts and the core self.
- Develop coping strategies that are tailored to the specific needs of each part and the system as a whole.
It’s crucial to remember that dissociation is a spectrum, and not everyone who experiences it has Dissociative Identity Disorder (DID). The model helps us understand the why behind these experiences, which can be incredibly validating for clients. Learning about Dissociative Identity Disorder explained can offer further insight into the more complex presentations of dissociation.
Collaboration and Ongoing Learning
Working with the structural dissociation model in Australia means I’m always learning. It’s a field that’s constantly evolving, and I find that connecting with other clinicians is invaluable. Sharing insights, discussing challenges, and learning from each other’s experiences helps us all refine our practice. This collaborative spirit is what makes our work here so rewarding. It’s about building a community of practice where we can support each other in supporting the people who come to us for help. We’re all on a journey of understanding, and that’s something to be celebrated.
The goal isn’t to eliminate the ‘parts’ but to help them work together more harmoniously, reducing distress and increasing a sense of wholeness for the person.
The Structural Dissociation Model is a way therapists in Australia understand how trauma can split a person’s mind. It helps them figure out how to best help people who have been through tough experiences. Want to learn more about how this model is used in real-life therapy sessions? Visit our website for more details.
Wrapping Things Up
So, that’s a bit of a look into the structural dissociation model. It’s a complex topic, for sure, and I’ve tried to break it down in a way that makes sense for us clinicians here in Australia. Remember, understanding this stuff isn’t about slapping labels on people; it’s about getting a clearer picture of how someone’s mind might be working, especially after tough experiences. It helps us be more thoughtful in our approach, whether we’re using talk therapy, IFS, or SFBT. Keep learning, keep asking questions, and let’s continue to support our clients with compassion and insight. I reckon we’re all doing some pretty important work out there.
Frequently Asked Questions
What exactly is the Structural Dissociation Model?
Basically, it’s a way to understand how people’s minds can split up, or ‘dissociate’, when they go through really tough or overwhelming experiences, especially when they’re young. It suggests that instead of one whole self, a person might develop different ‘parts’ or ‘alters’ to cope with different aspects of life or trauma. I find it helps me make sense of why some people experience the world in such a fragmented way.
Is dissociation the same as having Dissociative Identity Disorder (DID)?
Not quite. Dissociation is more like a spectrum. We all do it sometimes, like when we’re daydreaming or driving and zone out a bit. DID is at the extreme end of that spectrum, where the dissociation is so significant that distinct personality states or ‘alters’ emerge and take control. The model helps me see how DID can develop from severe trauma, but it also explains milder forms of dissociation too.
How does trauma lead to this ‘splitting’ of the self?
When a child experiences something too overwhelming to handle consciously, their mind might ‘split off’ the part that’s experiencing the trauma. It’s like a survival mechanism. If the trauma keeps happening, more parts might form to deal with different situations or feelings. The model explains this ‘splitting off’ as a way for the core self to be protected from unbearable pain.
What do you mean by ‘parts’ or ‘alters’?
These are the different aspects or ‘pieces’ of a person’s identity that have split off due to trauma. They might have different names, ages, memories, or ways of behaving. I think of them as different ‘versions’ of the person that developed to help them survive. My work often involves understanding and communicating with these different parts.
How do these ‘parts’ stay separate?
There’s often an ‘amnesiac barrier’ that keeps these different parts from knowing about each other. This means a person might have gaps in their memory, especially around the times when certain parts were active or when traumatic events occurred. It’s like each part lives in its own little world within the person’s mind.
Can this model help people who don’t have DID?
Absolutely! While the model is really useful for understanding DID, it also sheds light on many other experiences. Many people I work with, even without a DID diagnosis, experience symptoms like memory gaps, feeling disconnected from themselves, or having different ‘modes’ they go into. This model helps me understand those experiences too.
How do you work with these ‘parts’ in therapy?
My approach, drawing from therapies like Internal Family Systems (IFS), involves helping clients understand and communicate with their different parts. The goal isn’t necessarily to get rid of them, but to help them work together more harmoniously. We aim to build bridges between the parts and foster a sense of connection and integration, leading to healing.
What are some common signs that someone might be experiencing structural dissociation?
I often look for things like significant memory gaps, feeling like you’re not in control of your actions sometimes, hearing voices in your head (that aren’t from external sources), intense mood swings, or feeling detached from your body or surroundings. Sometimes people also experience flashbacks or have trouble concentrating, especially if trauma is involved.
Related Articles:
- Understanding and Navigating Treatment: How to Treat Dissociative Identity Disorder Effectively
- Unravelling the Mystery: What Causes Dissociative Identity Disorder?
- Understanding Dissociative Identity Disorder: A Guide for Australians
- Understanding Dissociative Identity Disorder: A Guide for Australians
- Understanding Trauma-based Mind Control: A Deep Dive
- Understanding the Alters in Dissociative Identity Disorder: A Comprehensive Guide
- Understanding Dissociative Identity Disorder (DID) Symptoms: A Guide for Australians
- Understanding Alters and Triggers within the MONARCH PROGRAMMING Framework
-
Understanding Dissociative Identity Disorder Symptoms: A Guide for Australians